When a large clot blocks an artery in the brain, medicines alone often cannot open it. In such cases, doctors can remove the clot directly with a procedure called mechanical thrombectomy. For the right patient, it can mean the difference between lifelong disability and walking out of the hospital.
In this blog, we explain when mechanical thrombectomy is used for stroke, who is eligible, how long after symptoms it can still help and what to expect.
What Is Mechanical Thrombectomy?
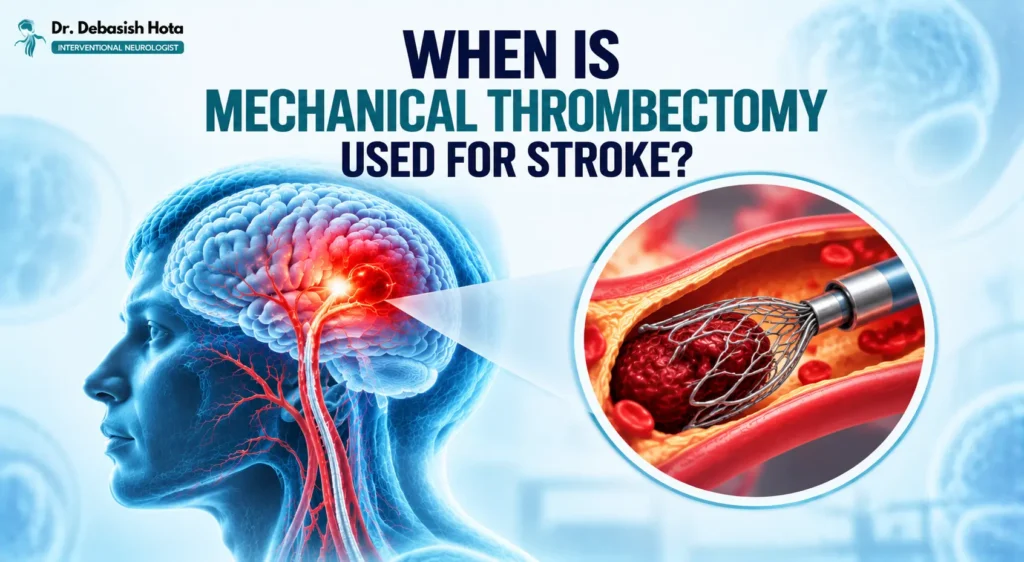
Mechanical thrombectomy is a minimally invasive procedure that removes a blood clot from a blocked brain artery. A thin tube (catheter) is passed through an artery, usually in the wrist or groin, and guided up to the brain under X-ray imaging. A small device then pulls out or sucks out the clot, and blood flow is restored.
There is no large cut on the head and no open brain surgery. The procedure is done by a specialist trained in neurointervention, usually under local anaesthesia with sedation, or sometimes under general anaesthesia.
When Is Mechanical Thrombectomy Used for Stroke?
Thrombectomy is mainly used in an ischemic stroke caused by a blockage in a large blood vessel of the brain. Doctors consider it when:
- A scan (CT angiography or MR angiography) confirms a large vessel occlusion (LVO), a blockage in a major brain artery
- The patient has significant stroke symptoms, such as marked weakness, speech loss or severe disability
- The patient reaches a hospital within the treatment window, or imaging shows brain tissue that can still be saved
- The patient was independent in daily life before the stroke
- The scan shows that the benefit outweighs the risk
It is a stroke treatment aimed at the most severe type of blockage, which is also the type that causes the most disability and death if left untreated.
Which Blockages Can Be Treated?
Thrombectomy works best when the clot is in a large, reachable artery. The commonly treated sites include:
- Internal carotid artery (ICA): the main artery supplying the front of the brain
- Middle cerebral artery (MCA, M1 and sometimes M2 segments): the most common site of large vessel stroke
- Basilar artery: a major artery at the back of the brain, where a blockage can be life-threatening
Clots in very small, deep vessels are usually not suitable because the catheter cannot reach them safely. These strokes are treated with medicines and supportive care.
What Is the Time Window for Thrombectomy?
Time matters, but the window is wider than many people think.
- Within 6 hours of symptom onset: this is the standard window, when most patients benefit.
- 6 to 24 hours: thrombectomy can still help selected patients, if advanced scans such as CT perfusion or MRI show that a good amount of brain tissue is still alive and can be saved.
- Unknown onset (for example, waking up with symptoms): the decision is made from the scan findings rather than the clock alone.
Even so, the earlier the clot is removed, the better the result. Doctors say “time is brain” because millions of neurons are lost every minute that a large artery stays blocked.
Which Scans Decide Eligibility?
Before thrombectomy, doctors usually do:
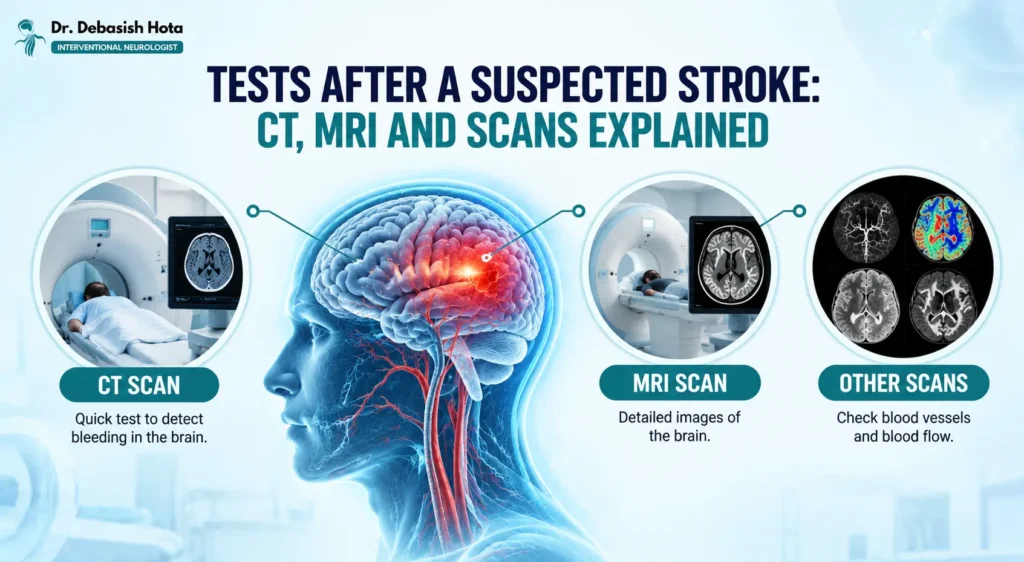
- Non-contrast CT: to rule out bleeding in the brain
- CT angiography: to find the exact blocked artery and check whether the clot can be reached
- CT perfusion or MRI: to measure how much brain is already damaged and how much can still be saved
In recent years, studies have shown that some patients with a larger area of damage can still benefit from thrombectomy, so the decision is made case by case by the stroke team.
Can Thrombectomy Be Combined With Clot-Dissolving Medicine?
Yes. If the patient arrives early and has no reason to avoid it, a clot-dissolving medicine (thrombolysis) is given through a vein while preparations for thrombectomy are made. The medicine may open some clots by itself, but large clots in big arteries often need to be removed mechanically. Both treatments work together and should not delay each other.
When Is Thrombectomy NOT Used?
Thrombectomy is not suitable for every patient. It is usually not done when:
- The stroke is caused by bleeding (hemorrhagic stroke), not a clot
- The blockage is in a very small or deep vessel that the catheter cannot safely reach
- The brain damage is already very extensive, with little tissue left to save
- Symptoms are very mild and the benefit is unlikely to outweigh the risk
- The patient was severely disabled before the stroke
- The clot has already opened by itself and blood flow has returned
In these cases, other treatments such as medicines, blood pressure control and rehabilitation are used.
How Is the Procedure Done?
- The patient is moved quickly to the angiography (cath) lab.
- A small puncture is made in an artery, usually in the groin or wrist.
- A catheter is guided through the blood vessels up to the blocked brain artery.
- A stent retriever (a tiny mesh device) or an aspiration catheter is used to trap and remove the clot.
- A final angiogram checks that blood flow has been restored.
- The patient is then shifted to the ICU or stroke unit for close monitoring.
The procedure often takes about one hour, though it can vary.
What Are the Benefits of Mechanical Thrombectomy?
For eligible patients with large vessel blockages, thrombectomy:
- Restores blood flow much more reliably than medicines alone
- Greatly improves the chance of living independently after a stroke
- Reduces long-term disability
- Can work even many hours after symptoms start, in selected patients
What Are the Risks?
Like any procedure, thrombectomy has risks. These include:
- Bleeding in the brain, which is uncommon but serious
- Injury to a blood vessel at the puncture site or in the brain
- The clot breaking into pieces and travelling to another vessel
- Reactions to the contrast dye or anaesthesia
- Clot returning in the same artery
The stroke team weighs these risks against the benefit before deciding. For most eligible patients, leaving a large blockage untreated carries a much higher risk than the procedure itself.
What Happens After Thrombectomy?
After the procedure, the patient is monitored closely in the ICU or stroke unit for 24 hours or longer. Blood pressure is carefully controlled, and a repeat scan checks for bleeding or swelling. Rehabilitation, such as physiotherapy, speech therapy and occupational therapy, begins as early as possible.
Long-term care focuses on finding the cause of the stroke and preventing another one, through medicines for blood pressure, cholesterol, blood sugar and blood thinning, along with lifestyle changes.
Why Does Reaching the Right Hospital Matter?
Not every hospital can perform thrombectomy. It needs a CT or MRI facility, an angiography lab and a trained team available round the clock. If you notice stroke symptoms, such as a drooping face, arm weakness or slurred speech, call for emergency help immediately and go to a stroke-ready hospital that has these facilities. Do not wait to see if the symptoms pass, and do not drive yourself.
When Should You Consult a Neurologist?
Seek emergency care for any sudden stroke symptoms. After the emergency, or if you have risk factors such as high blood pressure, diabetes, heart disease, irregular heartbeat or a previous mini-stroke, consult a neurologist to plan prevention and follow-up.
Final Thoughts
Mechanical thrombectomy is a powerful treatment for strokes caused by large clots in major brain arteries. It works best when the blockage is confirmed on a scan, the patient reaches a stroke-ready hospital quickly and enough brain tissue remains to be saved. Recognising the signs early and getting to the right hospital without delay gives the best chance of recovery.
Disclaimer: This blog is for general awareness only and does not replace professional medical advice. If you or someone near you shows signs of a stroke, seek emergency medical care immediately.
People Also Ask (FAQs)
When is mechanical thrombectomy done for stroke?
It is done for an ischemic stroke caused by a clot in a large brain artery, confirmed on a scan such as CT angiography. It is usually performed within 6 hours of symptoms, and in selected patients up to 24 hours, depending on how much brain tissue can still be saved.
How long after a stroke can thrombectomy be done?
The standard window is within 6 hours, but selected patients can be treated up to 24 hours after symptoms began or after they were last seen well, if advanced scans show salvageable brain tissue. Earlier treatment always gives better results.
Is mechanical thrombectomy a major surgery?
No. It is a minimally invasive procedure done through a small puncture in an artery, usually in the groin or wrist. There is no cut on the skull and no open brain surgery.
Can thrombectomy be done for a brain bleed?
No. Mechanical thrombectomy is used only for strokes caused by a blocked artery. Bleeding strokes are treated with other methods, such as blood pressure control, reversing blood thinners and, in some cases, surgery or procedures to treat the bleeding source.
What is the success rate of mechanical thrombectomy?
In most patients with large vessel blockages, the clot can be removed and blood flow restored in the large majority of cases. Results depend on how early treatment is done, the location of the clot and how much brain was damaged before the procedure. Your treating neurologist can explain what to expect in your case.